Sunday, August 9, 2026

Fusarium, the Microbiome, and the Many Possible Pathways of PATM

After years of collecting patient histories, correspondence, and laboratory reports, one impression has become increasingly difficult to ignore: there may not be one single underlying cause of PATM or MEBO. Instead, different people may arrive at a similar set of symptoms through different biological pathways.

We do have a growing list of possible culprits and triggers, and we are beginning to see that some patients can be matched by particular findings. But it remains a list—with many different candidates rather than one universal explanation. 

Last week, for example, we received a letter from a young woman in the United States who had experienced MEBO for approximately a decade. She was only recently diagnosed with biliary dyskinesia, a disorder affecting the movement of bile from the gallbladder.

This is not the first story of this type that we have encountered. In the past, we heard from a young man in China who had experienced PATM for approximately eight years and from a 37-year-old man in the United States who reported having PATM since he was 14. Both suspected problems with their gallbladder as a culprit.

These stories align with our observation that disturbances in different parts of the gastrointestinal system may sometimes contribute to a similar downstream phenomenon.

And then today, we received another intriguing history, this time from a man in Finland.

He believes that his PATM began following exposure to a water-damaged building and that Fusarium, a genus of fungi, may be involved.  Fusarium odoratissimum are explicitly named for their potent, recognizable odor and many strains produce damp, musty unpleasant smells. He subsequently had testing that detected mycotoxins associated with Fusarium, and he has developed a detailed hypothesis connecting fungal metabolism, intestinal processes, volatile organic compounds (VOCs), and the reactions experienced by people around him. This aligns with several other stories linked to mycotoxins, although those patients did not test specifically for fungi in their systems.

His interpretation is still a hypothesis. Nevertheless, Fusarium is another candidate that deserves to be investigated. 

Fungi and yeasts are still relatively understudied compared with bacteria, particularly when it comes to the human microbiome and gastrointestinal ecosystem.

At the same time, laboratory technology continues to evolve. Testing methods are becoming more sophisticated, and laboratories are expanding the range of microorganisms and metabolites they can detect.

That matters because what we are able to find depends, to some extent, on what we know how to look for.

The Finnish patient's testing was performed by Great Plains Laboratory, the same laboratory used by several other people in the PATM/MEBO community—along with Metametrix, Genova Diagnostics, Viome, and Biohm. We have not yet found one microorganism that is consistently present across all of these cases.

Interestingly, however, there are already some preliminary overlaps.

For example, among the people whose histories and laboratory results we have examined, Citrobacter freundii and E. coli have appeared in more than one case. These findings are far too limited to establish causation - both organisms can be found in the human gastrointestinal tract of individuals not reporting MEBO/PATM issues - but repeated observations are worth documenting and investigating.

Our microbiome study provides another piece of the puzzle. Using 16S rRNA sequencing, we found several microorganisms that appeared in common among participants. Some of these may represent opportunistic organisms or secondary changes resulting from another underlying disturbance, meaning that we may have been observing consequences rather than the original cause. I will be sharing more data from this study separately, but one important finding was the remarkably high heterogeneity among participants. Even with approximately 100 participants, the sample was not large enough to overcome that heterogeneity and identify a single consistent microbial signature.

This is another reason why I am increasingly hesitant to look for one universal culprit. The microorganisms we detect may sometimes be part of the downstream effects of whatever initially disrupted the individual's gastrointestinal ecosystem.

And Fusarium gives us yet another direction to explore.


PATM appears not to be a single disease with a single pathogen, but rather an umbrella for several conditions, just as similar symptoms in other medical conditions can arise from very different underlying problems.

One person might have a disorder affecting bile flow. Another might have bacterial dysbiosis. Another might have fungal involvement. Another might have a different gastrointestinal, metabolic, or systemic problem that we have not yet identified.

The common denominator may therefore not be the original cause, but rather what happens downstream.

Different disturbances could potentially alter the intestinal environment, microbiome, metabolism, or the volatile compounds released by the body. If those downstream changes are capable of producing similar external effects, they could potentially lead to what patients experience as PATM or MEBO.

Patient histories are not clinical trials, and an association between two findings does not establish causation. We also have to be careful with laboratory tests: detecting an organism, metabolite, or mycotoxin does not automatically tell us where it came from or whether it is responsible for someone's symptoms.

Nevertheless, patterns are worth recording.

If the same organism appears repeatedly in unrelated patients, that deserves investigation. If several people improve after treatment of a particular gastrointestinal disorder, that deserves investigation. If a fungal organism repeatedly appears in patients with similar symptoms, that deserves investigation too.

And if entirely different medical conditions appear to precede the same phenomenon, that may be an important clue in itself.

For now, our list remains a list.

But we might eventually map it to the different pathways that can lead to the PATM/MEBO phenomenon and to what those pathways have in common.


REFERENCES

Gabashvili IS  Cutaneous Bacteria in the Gut Microbiome as Biomarkers of Systemic Malodor and People Are Allergic to Me (PATM) Conditions: Insights From a Virtually Conducted Clinical Trial JMIR Dermatol 2020;3(1):e10508
URL: https://derma.jmir.org/2020/1/e10508
DOI: 10.2196/10508

MEBO and PATM--associated multispecies microbiomes mostly from stool, but also skin, oral, nasal, and genital sites   https://www.ncbi.nlm.nih.gov/sra?linkname=bioproject_sra_all&from_uid=1413303

Ledoux, M.-P., Dicop, E., Sabou, M., Letscher-Bru, V., Castelain, V., Danion, F., & Herbrecht, R. (2024). Fusarium, Scedosporium and Other Rare Mold Invasive Infections: Over Twenty-Five-Year Experience of a European Tertiary-Care Center. Journal of Fungi, 10(4), 289. https://doi.org/10.3390/jof10040289 


Thursday, August 6, 2026

Can Gallbladder Problems Cause Body Odor?

People living with persistent body odor or unexplained bad breath often search for answers beyond the skin and mouth. One organ that occasionally comes up in these discussions is the gallbladder. While gallbladder disease is not considered a common cause of chronic body odor, disorders affecting bile production and bile flow can contribute to digestive disturbances, changes in the gut microbiome, and, in some cases, unpleasant odors. As a matter of fact, one of such cases was described in medical literature in 1904. 

Understanding the connection begins with understanding what the gallbladder does.

The Gallbladder's Role

The gallbladder is a small organ located beneath the liver. It stores and concentrates bile, a digestive fluid produced by the liver that helps break down dietary fats and assists in the absorption of fat-soluble vitamins (A, D, E, and K). When you eat a meal containing fat, the gallbladder contracts and releases bile into the small intestine.

When this process is disrupted, digestion may suffer. Poor fat digestion can lead to gastrointestinal symptoms, changes in the intestinal microbiome, and altered metabolism—all of which may influence the production of odor-causing compounds.

Gallstones (Cholelithiasis)

Cholelithiasis refers to the formation of gallstones inside the gallbladder. Gallstones are usually composed of cholesterol, bilirubin pigments, or a mixture of both. They develop when bile contains too much cholesterol or bilirubin, too few bile salts, or when the gallbladder does not empty efficiently.

Many people with gallstones have no symptoms. Others experience:

  • Pain in the upper right abdomen, especially after fatty meals

  • Nausea and vomiting

  • Fever (if infection develops)

  • Jaundice

  • Bloating or indigestion

Some patients report unpleasant breath or body odor during symptomatic episodes. Although this is not a classic medical sign of gallstones, digestive stagnation, bacterial overgrowth, and impaired bile flow may increase the production of sulfur-containing compounds that smell like rotten eggs.

Stones in the Common Bile Duct (Choledocholithiasis)

Sometimes gallstones leave the gallbladder and become lodged in the common bile duct, blocking the flow of bile from the liver into the intestine.

Symptoms often include:

  • Severe abdominal pain

  • Nausea and vomiting

  • Fever

  • Jaundice

  • Dark urine and pale stools

This condition requires prompt medical evaluation because obstruction can damage the liver and pancreas or lead to infection.

Cholangitis

Cholangitis is an infection and inflammation of the bile ducts, usually caused by obstruction from a gallstone, although tumors or strictures can also be responsible.

Typical symptoms include:

  • Fever and chills

  • Right upper abdominal pain

  • Jaundice

Because bile is no longer flowing normally, digestion becomes impaired, and bacterial metabolism may change dramatically. Cholangitis is a medical emergency requiring immediate treatment with antibiotics and often procedures to relieve the obstruction.

Cholecystitis

Cholecystitis is inflammation of the gallbladder, most commonly caused by a gallstone blocking the cystic duct. Trapped bile causes irritation, swelling, and sometimes infection.

Symptoms include:

  • Persistent pain in the upper right abdomen

  • Fever

  • Nausea and vomiting

  • Tenderness over the gallbladder

Some people also report digestive symptoms such as constipation, bloating, bad taste in the mouth, bad breath, or increased body odor. Pale, greasy, or foul-smelling stools may occur when bile is not reaching the intestine normally.

Why Might Gallbladder Disease Affect Odor?

Several mechanisms have been proposed:

Changes in the gut microbiome. Reduced bile flow alters the intestinal environment. Bile normally helps regulate bacterial populations, so impaired bile secretion may allow certain bacteria to flourish. Even in the 1904 article about Cholelithiasis and Cholecystitis, a microbe Eberth's bacillus, was mentioned. It is the historical name for Salmonella typhi, the rod-shaped bacterium that causes typhoid fever. (that causes body odor to resemble freshly baked brown bread or warm, musty baked bread). But, of course, in most odor cases the responsible microbes are much more benign. 

Small intestinal bacterial overgrowth (SIBO). Poor bile flow can contribute to bacterial overgrowth in susceptible individuals. Some bacteria produce volatile sulfur compounds and other odor-causing metabolites.

Fat malabsorption. Inadequate bile impairs fat digestion, leading to fermentation of undigested nutrients and changes in stool odor.

Volatile metabolites. Researchers are increasingly studying volatile organic compounds (VOCs) produced by human metabolism and gut microbes. Alterations in bile acid metabolism may change the profile of VOCs released through breath, skin, urine, and stool, although much remains to be learned.

Does Gallbladder Removal Eliminate Body Odor?

Not necessarily.

Many people undergo cholecystectomy (gallbladder removal) and recover without digestive problems. Others continue to experience gastrointestinal symptoms because the underlying issue was not the gallbladder itself but rather changes in bile acid metabolism, the gut microbiome, liver function, or intestinal motility.

If body odor began before surgery and persists afterward, it may be worthwhile to investigate other contributing factors such as:

  • Small intestinal bacterial overgrowth (SIBO)

  • Bile acid malabsorption

  • Gut dysbiosis

  • Liver disease

  • Metabolic disorders

  • Trimethylaminuria or other rare metabolic conditions

When to Seek Medical Care

Seek prompt medical attention if gallbladder symptoms are accompanied by:

  • Fever or chills

  • Jaundice

  • Severe abdominal pain lasting several hours

  • Persistent vomiting

  • Confusion or low blood pressure

These symptoms may indicate an obstructed bile duct or cholangitis, both of which require urgent treatment.

The Bottom Line

Gallbladder disease is not a common cause of chronic body odor, but it can contribute indirectly through impaired bile flow, altered digestion, and changes in the gut microbiome. For some individuals, treating gallbladder disease improves digestive symptoms and associated odors. For others, persistent odor signals that additional metabolic or gastrointestinal factors remain to be investigated.

As research into metabolomics, the microbiome, bile acids, and volatile organic compounds continues to advance, we are gaining a better understanding of the complex relationship between digestion and body odor. Rather than viewing odor as an isolated symptom, it may be more helpful to consider it as one clue within a larger network of metabolic and gastrointestinal health.


REFERENCES

Chen Y, Weng Z, Liu Q, Shao W, Guo W, Chen C, Jiao L, Wang Q, Lu Q, Sun H, Gu A. FMO3 and its metabolite TMAO contribute to the formation of gallstones. Biochimica et biophysica acta (BBA)-Molecular basis of disease. 2019 Oct 1;1865(10):2576-85.

Sagar NM, Cree IA, Covington JA, Arasaradnam RP. The interplay of the gut microbiome, bile acids, and volatile organic compounds. Gastroenterology research and practice. 2015;2015(1):398585.

McDonald CM, Reid EK, Pohl JF, Yuzyuk TK, Padula LM, Vavrina K, Altman K. Cystic fibrosis and fat malabsorption: Pathophysiology of the cystic fibrosis gastrointestinal tract and the impact of highly effective CFTR modulator therapy. Nutrition in Clinical Practice. 2024 Apr;39:S57-77.

Stockton CG. Diagnosis of Cholelithiasis and Cholecystitis, with Remarks on Medical Treatment. Buffalo Medical Journal. 1904 Apr;43(9):573.

Stavropoulos G, van Munster K, Ferrandino G, Sauca M, Ponsioen C, van Schooten FJ, Smolinska A. Liver impairment—the potential application of volatile organic compounds in hepatology. Metabolites. 2021 Sep 11;11(9):618. 

http://www.bodyodor777.com 

Friday, May 15, 2026

What Is BM109?

Many people living with TMAU know how hard daily life can be.
The smell caused by the condition can affect friendships, work, school, relationships, and mental health. Some people feel isolated or hopeless because there are very few treatments available.

Now, there may finally be some hopeful news.

A biotechnology company called BioMe Inc. in Seoul, South Korea, has received approval from the U.S. Food and Drug Administration (FDA) to begin testing a new treatment called BM109 in real TMAU patients.

This is important because it means the treatment has moved beyond laboratory testing and is now entering human clinical trials.

BM109 is a new kind of treatment called a live biotherapeutic product (LBP).

That means it uses living helpful bacteria to improve health.

The bacteria used in BM109 is a naturally discovered bacteria called:

Paracoccus aminovorans

BioMe says these bacteria can:

  • Break down TMA

  • Break down TMAO

  • Help remove odor-causing chemicals from the body

The goal is simple:

Reduce the chemicals that cause the smell before they build up.

This is different from many current treatments that only try to manage symptoms.


The FDA has now allowed BM109 to move into Phase 1/2a clinical trials.

That means researchers will now test:

  • Safety

  • Side effects

  • Whether it actually helps TMAU patients

The studies will involve real people with TMAU, not healthy volunteers.

The trials will be led by researchers connected to:

  • Yale University

  • Mayo Clinic

These are respected medical institutions in the United States.

It is important to stay realistic.

BM109 is NOT approved yet.

The treatment is still being tested.

That means:

  • Nobody knows yet how well it will work

  • Nobody knows if it will work for everyone

  • It could still fail during trials

But this is still a very meaningful step because TMAU has received very little research attention for many years.

For many patients, simply seeing a treatment move into human trials brings hope.


BioMe says TMAO may also be connected to:

  • Heart disease

  • Stroke

  • Kidney disease

Because of this, the company hopes BM109 may someday help with those conditions too.

But right now, the main focus is TMAU.


BioMe is also working on another bacteria-based product called BM107A.

This product is being studied for:

  • IBS (irritable bowel syndrome)

  • Colon health

  • Constipation

  • Inflammation

  • Brain and cognitive health

It works differently from BM109 and focuses on producing a healthy substance called butyrate in the gut.


People with TMAU often feel ignored by the medical system.

Many have spent years searching for answers, support, and understanding.

While BM109 is still experimental, this news shows that researchers are finally taking TMAU more seriously.

For now, the best thing patients can do is stay informed, stay connected with support communities, and watch for future updates from clinical trials.

Hope may still be early - but it is real.

REFERENCES

You JS, Yoon CE, Kim JB, Alrahman MA, Jung HY, Yoon MY, Kim YB, Lee SG, Nam HS, Yoon SS. Microbiome-Targeted Reduction of Circulating Trimethylamine N-Oxide Mitigates Ischemic Stroke Risk. bioRxiv. 2026:2026-04.

Kim SH, Yoon MY, Yoon SS. TMAO and the gut microbiome: implications for the CVD-CKD-IBD axis. Annals of medicine. 2025 Dec 31;57(1):2522324.

https://biz.chosun.com/en/en-science/2026/05/11/6HY2VNJO55COHMPIAMHS3PSPYU/

Wednesday, April 15, 2026

Why Clean Clothes Still Smell

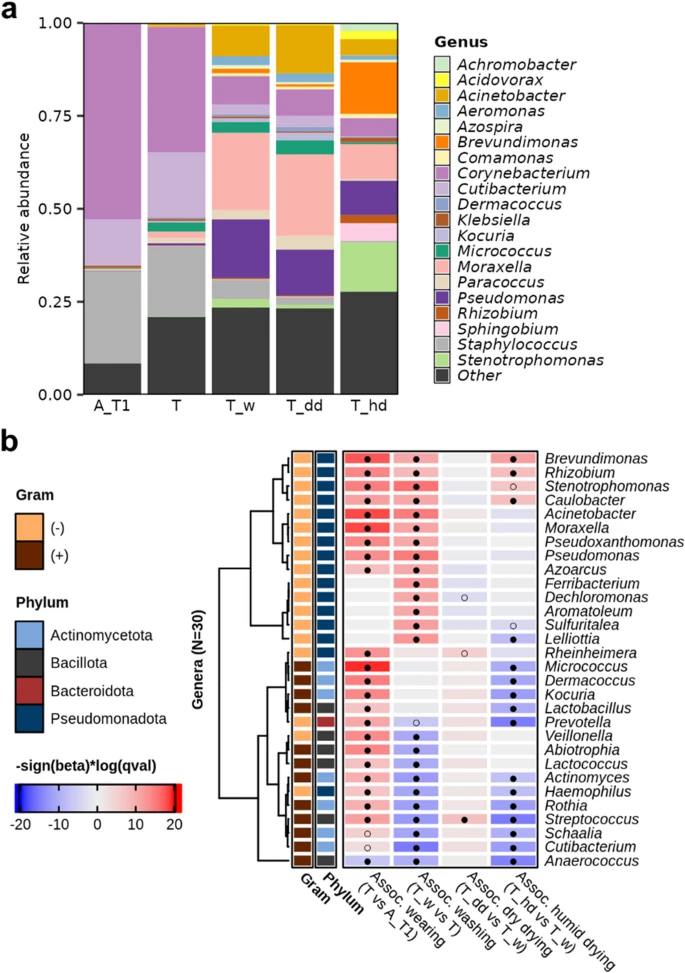
 A recent study in BMC Biology explored something many people quietly struggle with: why clothes can smell bad even after washing.

We know, it isn’t just sweat - it’s microbes.

  • Washing doesn’t fully remove bacteria—it can actually increase certain types of bacteria on clothes.
  • Your clothes pick up microbes not only from your body, but also from the washing machine and water.
  • Humid drying (slow drying in damp air) is a major problem—it allows bacteria to grow again and recreate bad smells.
  • Synthetic fabrics (like polyester) trap more odor-causing compounds than natural fabrics.

In simple terms:
๐Ÿ‘‰ You wash away odor… but bacteria come back - and if clothes stay damp, they multiply and produce smell again.


What helps

1. Dry clothes FAST

  • Don’t leave clothes sitting wet in the machine
  • Avoid indoor damp drying if possible
  • Use:
    • sunlight ☀️ (UV kills bacteria)
    • a dryer
    • or strong airflow

๐Ÿ‘‰ The study shows humid drying = more bacteria + worse smell


2. Use the right washing settings

  • Wash at higher temperatures (≥60°C when possible)
  • Use oxygen bleach or antibacterial detergents occasionally

๐Ÿ‘‰ Low-temp eco washes often leave bacteria behind


3. Choose better fabrics

  • Prefer:
    • cotton
    • wool
  • Be careful with:
    • polyester / gym wear (holds smell more)

4. Clean your washing machine

  • Run hot empty cycles regularly
  • Clean rubber seals
  • Leave the door open after use

๐Ÿ‘‰ Machines themselves are a source of odor bacteria


5. Use targeted products (if needed)

  • Enzyme detergents (break down sweat compounds)
  • Oxygen bleach (kills microbes)
  • Laundry sanitizers

๐Ÿ‘‰ Not always necessary—but helpful for persistent “permastink”


6. Don’t overload or delay laundry

  • Overloading reduces cleaning effectiveness
  • Letting clothes sit damp = bacteria growth

Going Deeper: What Actually Causes the Smell?

๐Ÿฆ  “Smelliest” bacteria aren’t just one group

The study shows that odor isn’t caused by a single species—it’s a community effect:

  • Skin-associated Gram-positive bacteria
    • e.g. Corynebacterium, Staphylococcus, Micrococcus (as also found in Gabashvili, 2020)
    • Key role: break down sweat into short-chain fatty acids (classic BO smell)
  • Environment-associated Gram-negative bacteria (after washing)
    • e.g. Pseudomonas, Acinetobacter, Moraxella
    • Key role: thrive in moist conditions and contribute to “musty” or “wet laundry” odours

๐Ÿ‘‰ Washing often replaces skin bacteria with environmental ones, rather than removing microbes entirely


๐Ÿงช The real culprits: volatile molecules (not just bacteria)

What we smell are volatile organic compounds (VOCs), especially:

  • 2- & 3-methylbutanoic acid → cheesy / sweaty
  • n-pentanoic, hexanoic acids → rancid / sour
  • aldehydes (like octanal) → fatty / “post-wash” smell

These molecules:

  • disappear after washing
  • reappear during humid drying due to bacterial metabolism

๐Ÿง  Why single-method science falls short

❌ Sequencing alone is not enough

Metagenomics tells you:

  • who is there

But not:

  • what they are actively doing
  • which ones are producing odours

๐Ÿ‘‰ The paper shows huge taxonomic shifts (who’s present changes a lot)


❌ Metabolites alone are not enough

Chemical analysis (VOCs) tells you:

  • what smells are present

But not:

  • which microbes produced them
  • how environmental conditions shaped them

๐Ÿ”— The key insight: function ≠ identity

One of the most interesting findings:

  • Microbial composition changes a lot
  • Functional pathways stay relatively stable

๐Ÿ‘‰ Different bacteria can produce the same smelly compounds

This is called functional redundancy.


๐Ÿงฌ Why multi-omics is essential

To truly understand laundry malodour, you need:

1. Metagenomics

  • Identify microbial community
  • Track shifts (skin → machine microbes)

2. Metabolomics / GC-MS

  • Identify actual odour-causing compounds

3. Quantitative methods (e.g. flow cytometry)

  • Measure bacterial load changes

4. Environmental context

  • Temperature
  • Humidity
  • Fabric type

๐Ÿ’ก Research implications

  • Designing detergents should target functions (metabolism, biofilms), not just species
  • Drying conditions may be as important as washing chemistry
  • Future work:
    • transcriptomics (gene activity)
    • real-time VOC tracking
    • biofilm disruption strategies
REFERENCES

Dรญez Lรณpez, C., Van Herreweghen, F., De Pessemier, B. et al. Unravelling the hidden side of laundry: malodour, microbiome and pathogenome. BMC Biol 23, 40 (2025). https://doi.org/10.1186/s12915-025-02147-5

Gabashvili IS Cutaneous Bacteria in the Gut Microbiome as Biomarkers of Systemic Malodor and People Are Allergic to Me (PATM) Conditions: Insights From a Virtually Conducted Clinical Trial JMIR Dermatol 2020;3(1):e10508  doi: 10.2196/10508

Monday, January 5, 2026

Research Over Despair

I am always glad to receive letters from people who, despite facing real difficulties, are motivated to understand their condition and actively look for solutions. This letter was one of those.

It came from a young person who had lived with PATM (People Allergic to Me) for just over a year. In that short time, the condition had disrupted education, lab work, friendships, and mental health. Like many others with PATM, this individual had been told - explicitly or implicitly - that what they were experiencing might not be real.

What struck me most was not the suffering (which, sadly, is familiar), but the decision that followed: instead of giving up, they chose to learn, to research, and to ask whether science might eventually provide answers - not only for themselves, but for others.

Below is a modified, bulletized and anonymized version of my response to their questions, shared here because many patients ask the same things.


Why is PATM still an undiagnosed condition?

PATM is often described as “undiagnosed,” but a more accurate term would be not formally recognized.

For a condition to become a recognized clinical entity, several things usually need to be in place:

  • a consistent case definition

  • reproducible, objective measurements

  • and a plausible pathophysiological mechanism that can be validated by multiple independent groups

At present, PATM does not yet meet all of these thresholds.

One major challenge is heterogeneity. The presentation varies widely from person to person, and triggers differ depending on environment, exposure, and individual biology. Another major obstacle is that current clinical workflows are poorly suited to capture intermittent, airborne chemical events. Many patients describe symptoms that occur in bursts—so a clinical visit may appear “normal,” even when the lived experience is not.


What would it take to achieve a formal medical diagnosis?

Large clinical trials can help, but they are rarely the starting point.

The real bottlenecks are:

  • reproducible measurement methods

  • defining subtypes rather than assuming a single mechanism

  • capturing the episodic (“bursty”) nature of emissions

A well-designed, multicenter observational study—with standardized sampling protocols and careful timing relative to symptoms—may be a more realistic bridge step than jumping directly to intervention trials.

An official diagnosis could be beneficial. It can legitimize patients’ experiences in clinical settings, redirect care away from reflexive psychologization and attract more serious research attention. But such a diagnosis has to be built on solid evidence to endure.


Is toluene the main irritation-causing substance?

It is unlikely that there is a single universal compound responsible for PATM.

Research on skin gas emission profiles is important because it demonstrates measurable chemical differences, but the broader picture likely involves multiple emitted mixtures and multiple subtypes. In some individuals, compounds such as toluene or related aromatics may contribute to irritation-like symptoms; in others, different chemical patterns may dominate.

Another key factor may be differences in detoxification or clearance. Some people appear more susceptible to everyday exposures—such as secondhand smoke, solvents, or indoor VOCs—not because exposure is higher, but because metabolism and elimination differ.


What can patients realistically try on their own?

I generally recommend starting with low-risk, high-information approaches:

Structured symptom and exposure logging

Tracking timing, diet, stress, environment (workplace, vehicles, indoor air), laundry and personal care products, and proximity to smoke or solvents can help identify repeatable patterns.

Basic medical rule-outs

Even when PATM is the primary concern, it is important to evaluate common contributors to odor or irritation-related conditions, such as reflux, sinus disease, metabolic or endocrine issues, liver and kidney function, medication effects, and dermatologic conditions.

Environmental controls

VOC-related problems are often exposure-amplified. Fragrance-free products, avoiding solvent-heavy cleaners, improving ventilation, and using HEPA plus activated carbon filtration can reduce background “noise” and make patterns easier to recognize.

I generally advise caution with high-risk or expensive interventions unless there is a clear rationale for a particular subtype.


What about fecal microbiota transplants (FMT)?

FMT is scientifically interesting but should be approached with caution. It is not a general solution for PATM and carries nontrivial risks. If considered at all, it should be under appropriate medical supervision and based on a specific, individualized hypothesis—not as a last-resort experiment.


Are microbiome or skin-gas profiling tests useful?

They can be, if used carefully.

  • Gut microbiome profiling may provide clues, but interpretation is still limited and should always be paired with symptom timelines, diet, and repeat measurements.

  • Skin or exhaled gas profiling is conceptually promising because it targets the suspected output directly. However, episodic emissions make timing critical, and passive sampling methods may miss short-lived events.

The usefulness depends less on the technology itself and more on study design.


Would wearable or portable gas sensors help?

In principle, yes. Continuous or frequent measurement could finally correlate chemical signatures with symptoms and environmental context.

In practice, true GC–MS–grade performance in a wearable format remains extremely challenging. Field measurements are complicated by changing ambient air, and episodic emissions require high time resolution and careful baseline correction. The idea is sound; the technology is still catching up.


Could funding agencies support this kind of work?

Possibly more so now than in the past.

Historically, conditions that primarily affect quality of life rather than mortality have struggled to gain funding. When I first applied for support nearly two decades ago, the problem was explicitly described as “not important enough.”

Today, there is broader recognition of the impact of stigma, mental health, and chronic quality-of-life impairment. Advances in exposomics, microbiome science, and wearable sensing technologies make it easier to frame this work as high-risk, high-reward, particularly if the focus is on measurement platforms, subtyping, and mechanism rather than a single compound.


Much of this may sound like a list of obstacles. But compared with even a decade ago, the path forward is clearer.

If PATM turns out not to be one condition but a family of related ones, that is not a failure of science—it is a more accurate description of biology. Progress will likely come not from searching for a single universal cause, but from building frameworks that can accommodate diversity, intermittency, and complexity.

And sometimes, progress begins with a patient who decides that understanding is better than silence.

Sunday, October 19, 2025

Diets That Dial Down TMA (and TMAO): What Latest Studies Suggest

This week's TL;DR: Diets that are high in fiber and lower in animal protein, plus Mediterranean-style eating, are emerging as the most food-first ways to reduce gut production of trimethylamine (TMA) and its oxidized form TMAO. Early evidence also points to targeted botanicals and postbiotics as promising add-ons - especially for people with heart or kidney concerns. If you live with MEBO/TMAU, the same general principles may apply.  

What seems to help most

1) High-fiber, lower-protein patterns (especially for CKD).
A fiber-rich, modest-protein intake can rebalance gut microbes and lower circulating TMAO in chronic kidney disease. Think: loads of vegetables, legumes, whole grains, nuts/seeds—while keeping total protein moderate and favoring plant sources. (Udomkarnjananun et al., 2025)

2) Mediterranean diet (MED).
A short, 4-week MED intervention—vegetables, fruits, legumes, whole grains, olive oil, nuts; limited red/processed meat—significantly reduced blood TMAO, even in healthy adults. Men in the study also saw better lipids and anthropometrics. (Deniz & BaลŸ, 2025)
Since fish contains pre-formed TMAO that can worsen odor in TMAU, adapt a fish-free Mediterranean pattern if you’re sensitive.

3) Botanicals with gut–heart effects (CHF).
In patients with chronic heart failure, the Chinese botanical formula Qili Qiangxin (QLQX) reduced BNP, TNF-ฮฑ, IL-6, and TMAO, pointing to lower systemic inflammation and improved barrier function. Food pattern still matters, but this suggests a potential adjunct under medical guidance. (Zhu et al., 2025)

Qiliqiangxin consists of extracts from eleven traditional Chinese medicinal herbs including for example: Panax ginseng  (ginseng), Astragalus mongholicus  (Mongolian milkvetch), Salvia miltiorrhiza (red sage), Cinnamomum cassia (cinnamon twig), Aconitum carmichaelii (Chinese aconite root), Descurainia sophia (flixweed), Periploca sepium (Chinese silkvine root bark), Alisma plantago-aquatica subsp. orientale (Oriental waterplantain), Carthamus tinctorius (safflower), Polygonatum odoratum (Angular Solomon's seal), and Citrus reticulata (dried mandarin peel)

4) Postbiotics (preclinical but intriguing).
In a choline-boosted, high-fat mouse model of atherosclerosis, Weizmannia coagulans JA845 postbiotics (based on B. coagulans JA845) lowered TMAO, improved the microbiome profile, dampened JAK/STAT3 inflammation, and protected vessels. Human data are pending, but this supports the microbiome-modulation avenue alongside diet. (Ma et al., 2025)

Unlike probiotics (which are live microorganisms) and prebiotics (which are food/substrates that feed beneficial microbes), postbiotics are non-live microbial cells, microbial cell parts, or microbial metabolites (or a mix) that can have beneficial effects. 

Example components might include dead/inactivated bacterial cells, cell wall fragments, microbial metabolites like short-chain fatty acids (SCFAs: butyrate, acetate, propionate), peptides and enzymes.


REFERENCES 

Udomkarnjananun S, Chuaypen N, Metta K, Dissayabutra T, Sodsai P, Kittiskulnam P, Tangkijvanich P. Dietary composition modulate gut microbiota and related biomarkers in patients with chronic kidney disease. Sci Rep. 2025 Oct 16;15(1):36274. doi: 10.1038/s41598-025-20266-5. PMID: 41102296; PMCID: PMC12533112. 

Zhu F, Hu R, Lv C, Wang J, Du X, Zeng X, Huang Y, Ma Y, Yang C, Guo F. Qili Qiangxin ameliorates chronic heart failure: a randomized clinical trial of biomarkers, inflammation, and cardiac outcomes. Front Pharmacol. 2025 Sep 30;16:1605944. doi: 10.3389/fphar.2025.1605944. PMID: 41098835; PMCID: PMC12518405. 

Deniz Mลž, BaลŸ M. Short-Term Mediterranean Dietary Intervention Reduces Plasma Trimethylamine-N-Oxide Levels in Healthy Individuals. Nutrients. 2025 Sep 30;17(19):3135. doi: 10.3390/nu17193135. PMID: 41097210; PMCID: PMC12525710. Ma L, Li N, Zhao Z, Zhao Y, 

Yang G, Zhao L, Li S. Weizmannia coagulans JA845 Postbiotics Alleviate Atherosclerosis via TMAO-Related Gut Microbiota Regulation and JAK/STAT3 Pathway Inhibition. Nutrients. 2025 Sep 23;17(19):3027. doi: 10.3390/nu17193027. PMID: 41097105; PMCID: PMC12526339.

Wednesday, August 13, 2025

AI meets MEBO

After a bit of a break since our first podcast back in March, we’re excited to return with a brand new episode for the MEBO and PATM community.

In this video, we’re exploring a big question: Can patients themselves use AI to help uncover potential causes, connections, and treatments for their symptoms?

The episode was generated by NotebookLM, based on our own research and the outputs of multiple large language models answering real questions from patients and researchers about these conditions. It’s a very good discussion overall - balanced, empathetic, and realistic about the challenges - but there are a few small hiccups.

For example, the video says that the paper "Cutaneous Bacteria in the Gut Microbiome as Biomarkers of Systemic Malodor and People Are Allergic to Me (PATM) Conditions" was published in Frontiers in Psychiatry in 2022. In fact, it appeared in JMIR Dermatology, a peer-reviewed journal, but one that isn’t indexed in PubMed - so it often doesn’t register in medical literature searches. Interestingly, when we asked half a dozen more LLMs about this paper, none knew much about it. Some even called it “groundbreaking” or “a beacon” without actually having the details, and a few hallucinated links that don’t exist.

PATM and MEBO are still often misclassified or linked to Olfactory Reference Syndrome, but there is growing recognition that underlying microbial dysbiosis or metabolic disorders may play a role.

Still, the bigger picture is encouraging: LLMs are improving, and that gives hope for people living with under-researched, heterogeneous, and often misunderstood conditions. While this podcast focuses a bit more on social and emotional support than on treatment options, that’s also an essential part of living with these conditions - and it makes this video worth watching.

Let’s dive in and see what AI can - and can’t - offer us right now.


get New Posts by EMAIL : Enter your email address :


A EURORDIS and NORD Member Organization

Friday, July 11, 2025

Can gut health really be the missing piece?

On February 17, 2025, reddit user iamjohnni  claimed on Reddit that they finally overcame years of chronic digestive issues, body odor (TMAU2), and PATM after a long journey of trial and error.

Their story began after taking antibiotics, which they believe disrupted their gut microbiome. For years they experienced IBS symptoms, bloating, brain fog, and body odor that severely affected their personal and professional life. Despite seeing multiple doctors and trying countless diets and supplements, nothing seemed to help.

The turning point, according to the post, came after completing a comprehensive GI-MAP stool test that identified gut dysbiosis, H. pylori, bacterial imbalances, and other digestive issues. Working with a healthcare professional, they followed a structured gut-healing protocol focused on:

✅ Eliminating harmful bacterial overgrowth
✅ Supporting digestion
✅ Rebuilding beneficial gut bacteria
✅ Repairing the gut lining

They reported that within several weeks, their digestion improved dramatically, brain fog disappeared, and the odor symptoms they had struggled with for years eventually resolved.

While this is just one person's experience—not scientific proof or a guaranteed treatment—it highlights an important point:

The gut microbiome plays a much larger role in overall health than many people realize.

Every person is different, and what works for one individual may not work for another. But stories like this remind us that persistent symptoms deserve thorough investigation rather than dismissal.

As research into the microbiome continues to grow, personalized approaches to gut health may become increasingly important for managing complex conditions.

Have you seen similar stories about gut health transforming chronic symptoms? I'd love to hear your thoughts and experiences.

Wednesday, April 16, 2025

The Smell of Life

Sulfur-rich smells are easy to recognize—think of the ocean at low tide, a bit of garlic, or even bad breath. While not always pleasant, they’re often tied to life processes. On Earth, compounds like dimethyl sulfide (DMS) and dimethyl disulfide (DMDS) are made by microbes, plants, and even our own bodies. For example, DMS is a byproduct of marine algae, and both DMS and DMDS are linked to the metabolism of sulfur-containing foods like garlic and onions.   

Interestingly, these same compounds can also show up when organic matter breaks down. Over time, the mix of smells changes—starting with more sulfur notes like DMDS and shifting toward other compounds like ketones and acids. But in the early stages, it’s sulfur that dominates the scent, reinforcing that these molecules are deeply tied to life, not just what comes after it.

They even show up in everyday biology—DMS contributes to halitosis (bad breath), and sulfur compounds in urine can reveal what you’ve eaten recently, like garlic or leeks. And while they can be a nuisance in places like sewers due to their strong odor and reactivity, these volatile sulfur compounds are powerful chemical clues that life is (or was) at work.


Reported Sensory Thresholds for Sulfur Compounds
CompoundStructureSensory DescriptionRange (ppb)
hydrogen sulfideH2Srotten egg, sewage-like0.9 - 1.5
ethyl mercaptanCH3CH2SHburnt match, sulfidy, earthy1.1 - 1.8
methanethiol, methyl mercaptanCH3SHskunk, flatulence, rotten cabbage, burnt rubber1.5
diethyl sulfideCH3CH2SCH2CH3rubbery0.9 - 1.3
DMS, dimethyl sulfideCH3SCH3ocean, canned corn, cooked cabbage, asparagus17- 25
diethyl disulfideCH3CH2SSCH2CH3garlic, burnt rubber3.6 - 4.3
DDMS, dimethyl disulfideCH3SSCH3vegetables, cabbage, onion-like at high levels9.8 - 10.2
carbon disulfideCS2sweet, ethereal, slightly green, sulfidy5


Imagine cracking open a clam at low tide or walking through a marsh at dusk. The faint, tangy smell of sulfur in the air? That’s dimethyl sulfide (DMS), a molecule born of life. It’s a scent tied to oceans, microbes, and biology itself.

Now picture that same signature—those familiar chemical traces—not wafting from Earth’s shoreline but drifting through the atmosphere of a distant world. That’s exactly what a team of astronomers, led by Nikku Madhusudhan at the University of Cambridge, believe they may have found.

Using the James Webb Space Telescope (JWST), they detected not only dimethyl sulfide (DMS) but also dimethyl disulfide (DMDS) in the atmosphere of exoplanet K2-18b orbiting a star 124 light-years away. On Earth, these molecules are exclusively produced by living organisms, especially marine phytoplankton and sulfur-reducing microbes.

Is this the first scent of alien life?

K2-18b has long intrigued scientists. Discovered in 2015 and confirmed to host water vapor in its atmosphere by 2019, it lies in the habitable zone of its star—a region where liquid water could exist. The planet is a sub-Neptune, about 8 times the mass of Earth, likely hosting a vast ocean beneath a hydrogen-rich sky.

When JWST's near-infrared instrument first picked up hints of DMS, the signal was tantalizing but faint. Now, using its mid-infrared camera, a much stronger signal has emerged—not just for DMS, but for DMDS, a closely related molecule. Both are complex sulfur-containing compounds known to be byproducts of living metabolic processes—especially those involving the breakdown of dimethylsulfoniopropionate (DMSP), an osmolyte made by marine algae.

On Earth, the sulfur cycle involves a complex web of microbial transformations, particularly in anoxic oceanic zones. Phytoplankton produce DMSP as a way to handle osmotic stress; when grazed by zooplankton or lysed by viruses, DMSP is broken down into DMS. Other microbes metabolize sulfur compounds into DMDS, H₂S, and others.

If such a cycle—or something like it—exists on K2-18b, it would suggest a complex biosphere, not just isolated organisms.

But here's the rub: abiotic pathways for these molecules must be explored and excluded. Could volcanic activity, UV-driven chemistry, or some exotic atmospheric process generate DMS or DMDS in a hydrogen-rich atmosphere? Theoretical chemists are scrambling for answers.

So, caution remains the astronomer's motto. The team stresses that while the signal is the strongest yet, non-biological explanations must be thoroughly ruled out before claiming even the possibility of life.

A molecule that, on Earth, rises from algae-covered oceans, has now risen from the atmosphere of a distant world. Whether this is truly life, or an undiscovered quirk of chemistry, remains to be seen.

But for the first time, astronomy is starting to smell like biology.


REFERENCES

Srila W, Sripilai K, Binlateh T, Thammanichanon P, Tiskratok W, Noisa P, Jitprasertwong P. Relationship Between the Salivary Microbiome and Oral Malodor Metabolites in Older Thai Individuals with Periodontitis and the Cytotoxic Effects of Malodor Compounds on Human Oral Squamous Carcinoma (HSC-4) Cells. Dentistry Journal. 2025 Jan 16;13(1):36.

Dekeirsschieter J, Stefanuto PH, Brasseur C, Haubruge E, Focant JF. Enhanced characterization of the smell of death by comprehensive two-dimensional gas chromatography-time-of-flight mass spectrometry (GCxGC-TOFMS). PLoS One. 2012;7(6):e39005. doi: 10.1371/journal.pone.0039005. Epub 2012 Jun 18. PMID: 22723918; PMCID: PMC3377612.

Madhusudhan, Nikku; et al. (March 2020). "The Interior and Atmosphere of the Habitable-zone Exoplanet K2-18b". The Astrophysical Journal Letters. 891 (1). L7. arXiv:2002.11115. doi:10.3847/2041-8213/ab7229

Schmidt SP, MacDonald RJ, Tsai SM, Radica M, Wang LC, Ahrer EM, Bell TJ, Fisher C, Thorngren DP, Wogan N, May EM. A Comprehensive Reanalysis of K2-18 b's JWST NIRISS+ NIRSpec Transmission Spectrum. arXiv preprint arXiv:2501.18477. 2025 Jan 30. arXiv:2501.18477 [astro-ph.EP]  https://doi.org/10.48550/arXiv.2501.18477

Ma J, Han Y, Ge J, Wen L, Ma C, Qi Y, Volmer DA. Comprehensive Two‐Dimensional Gas Chromatography–Mass Spectrometry for the Analysis of Atmospheric Particulate Matter. Rapid Communications in Mass Spectrometry. 2025 Jul 15;39(13):e10034.

Thursday, April 3, 2025

The Invisible Scent: Gut Microbes, Metabolism & MEBO


Welcome to The Invisible Scent, the podcast on the hidden connections between gut bacteria, metabolism, and socially debilitating malodor conditions like PATM, MEBO and TMAU. 

With expert interviews, patient stories, and cutting-edge insights, The Invisible Scent seeks to bridge the gap between medical research and real-world experiences. By embracing patient-reported data and advancing diagnostic tools, we aim to pave the way for more effective treatments and better quality of life for those affected.

Overview of MEBO/PATM and TMAU studies

get New Posts by EMAIL : Enter your email address :


A EURORDIS and NORD Member Organization

Sunday, February 23, 2025

From 4R to 5R: The Evolution of Functional Medicine in Gut Health

Functional medicine provides a powerful model known as the 5R Approach (Kim, 2024), which builds on the original 4R framework (Remove, Replace, Reinoculate, and Repair; Liลกka, 2003)) by adding a crucial final step: Rebalance.

This method is particularly valuable in treating gut dysbiosis, a condition in which the ratio of beneficial and harmful bacteria in the intestine is disrupted, leading to inflammation, poor digestion, and systemic health issues. Research has linked gut dysfunction to chronic conditions such as rheumatoid arthritis, eczema, and neurological disorders (Liลกka, 2003) as well as nonsyndromic body odor (Gabashvili, 2020)  


1. Remove: Eliminating Triggers of Gut Dysfunction

The first step in healing the gut is removing harmful elements that contribute to dysbiosis and inflammation. These include:

Pathogens – Overgrowth of harmful bacteria, yeast (Candida), or parasites.

Inflammatory Foods – Processed sugars, refined carbohydrates, artificial additives, and common allergens (gluten, dairy, soy).

Toxins & Medications – Overuse of antibiotics, NSAIDs, and environmental toxins disrupt gut flora and damage the mucosal lining.

๐Ÿ“Œ An elimination diet can help identify specific food triggers. GI map test as well as testing for known gut infections (such as H.pylori, HSV, CMV, giardia or Candida spp.) can also guide targeted interventions.


2. Replace: Supporting Digestive Function

Once harmful elements are removed, the next step is to restore digestive efficiency by supplying essential compounds for proper digestion:

Digestive Enzymes – Help break down food and enhance nutrient absorption.

Stomach Acid (HCl) – Supports protein digestion and prevents bacterial overgrowth.

Bile Salts – Assist in fat digestion and absorption, especially if gallbladder function is compromised.

๐Ÿ“Œ Consider incorporating enzyme-rich foods like papaya (papain) and pineapple (bromelain) or taking targeted supplements.

3. Reinoculate: Restoring Beneficial Bacteria

A diverse microbiome is essential for digestion, immunity, and gut-brain interactions. Research suggests that early-life gut health, influenced by factors like breastfeeding, can impact long-term microbial balance (Ley et al., 2021).

๐Ÿ“Œ Aim for a variety of fiber-rich foods, prebiotics (asparagus, bananas, onions) and probiotic-rich fermented foods to support microbiome diversity, rather than relying solely on probiotic supplements. 


4. Repair: Healing the Gut Lining

An increase in harmful bacteria can damage the intestinal mucosal cells, contributing to leaky gut syndrome and systemic inflammation (Kim, 2024). Repairing the gut lining is crucial for long-term resilience.


Key nutrients that aid gut repair include:

L-glutamine – An amino acid essential for intestinal wall regeneration.

Collagen & Bone Broth – Provide glycine and proline, which strengthen the gut barrier.

Zinc & Vitamin A – Promote mucosal healing and immune function.

Omega-3 Fatty Acids – Reduce inflammation and support tissue repair.


5. Rebalance: Addressing Lifestyle Factors

The final and often overlooked step in gut healing is rebalance—restoring the mind-body connection and lifestyle habits that influence digestive health. The gut-brain axis plays a crucial role in regulating digestion, with parasympathetic “Rest and Digest” responses supporting motility and secretions (Gantzer, 2021).


To rebalance:

Stress Management – Chronic stress disrupts gut function and increases inflammation. Practices like meditation, deep breathing, and yoga enhance parasympathetic regulation.

Sleep Quality – Poor sleep affects gut motility and microbiome balance. Aim for 7-9 hours of uninterrupted sleep.

Physical Activity – Moderate exercise supports gut health by improving motility and microbiome diversity.

๐Ÿ“Œ Engage in mindful eating—slow down, chew thoroughly, and avoid distractions to support optimal digestion.


The 5R Approach offers a structured, evidence-based method for restoring gut health and preventing chronic disease. Whether dealing with digestive disorders, autoimmunity, or general well-being, this framework provides a sustainable path to healing.

By removing harmful triggers, replacing digestive supports, reinoculating the microbiome, repairing the gut lining, and rebalancing lifestyle factors, we can achieve long-term gut resilience and overall health.


REFERENCES

Gabashvili IS Cutaneous Bacteria in the Gut Microbiome as Biomarkers of Systemic Malodor and People Are Allergic to Me (PATM) Conditions: Insights From a Virtually Conducted Clinical Trial JMIR Dermatol 2020;3(1):e10508 doi: 10.2196/10508

๊น€๊ทœ๋‚จ. ๊ธฐ๋Šฅ์˜ํ•™์  5R ์น˜๋ฃŒ์˜ ๊ทผ๊ฑฐ์™€ ์ ์šฉ. Journal of Korean Institute for Functional Medicine. 2024 May;7(1):1-8: Kyu-Nam Kim  Korean Society of Functional Medicine Journal of Korean Institute for Functional Medicine Vol.7 No. 1 2024.05 1 - 8 (8 pages) DOI : 10.32581/jkifm.2024.7.1.1

Liska DJ, Lukaczer D. Gut dysfunction and chronic disease: the benefits of applying the 4R GI restoration program. ANSR-Appl Nutr Sci Rep. 2003:1-8.

J. Gantzer Acta Supporting Gut Health by Homeostasis and Intrinsic Mechanisms. Scientific Neurology 1 November 2021 https://www.actascientific.com/ASNE/pdf/ASNE-04-0444.pdf

Tuesday, December 31, 2024

Sniffing Out Stress: Odor Profiling as a Tool for Health Monitoring

Recent research paper highlights the potential of manure odor profiling as a non-invasive tool for monitoring stress and intestinal health in poultry flocks. Using advanced gas chromatography-mass spectrometry, scientists analyzed volatile compounds in manure from layer pullets undergoing routine vaccinations, such as Salmonella and viral/bacterial vaccine cocktails. These vaccinations served as model stressors.  

Key findings include:

  • Age Matters: Young and older pullets displayed distinct volatile profiles. Compounds like beta-camphor and (Z)-6-Tridecene were elevated in younger birds, while carbonyl sulfide and trimethylamine dominated in older ones.
  • Vaccine Impact: The Salmonella vaccine elicited the most consistent changes in manure volatiles, particularly in younger birds, while the viral/bacterial cocktail caused more pronounced shifts in older birds.
  • Consistency: Despite differences in age, housing, and vaccine type, reductions in certain volatile intensities (e.g., (Z)-6-Tridecene) were observed in three of four flocks post-vaccination.

This approach could pave the way for precision livestock farming, offering an objective means of monitoring flock-level responses to stressors and intestinal health challenges.

Interestingly, trimethylamine (TMA)—a volatile compound detected in older pullets—plays a significant role in both poultry manure profiling and human health. Recent research identified the bacterium JAGTTR01 sp018223385 as a key player in producing TMA from L-carnitine in the human gut. Elevated TMA levels, when metabolized into trimethylamine N-oxide (TMAO), are linked to cardiovascular risks.

The overlap underscores the broader potential of olfactory diagnostics in understanding microbial activity and health impacts across species. Whether in poultry farms or human health, volatile profiling reveals a fascinating connection between microbial metabolism, diet, and well-being.


REFERENCES

van Veen LA, van den Brand H, van den Oever ACM, Kemp B, Meisenburg M. Manure odor profiling for flock-level monitoring on commercial layer pullet farms: Vaccination events as a model stressor. Poult Sci. 2024 Dec 16;104(2):104681. doi: 10.1016/j.psj.2024.104681. Epub ahead of print. PMID: 39721281.

Wu WK, Lo YL, Chiu JY, Hsu CL, Lo IH, Panyod S, Liao YC, Chiu THT, Yang YT, Kuo HC, Zou HB, Chen YH, Chuang HL, Yen JJY, Wang JT, Chiu HM, Hsu CC, Kuo CH, Sheen LY, Kao HL, Wu MS. Gut microbes with the gbu genes determine TMAO production from L-carnitine intake and serve as a biomarker for precision nutrition. Gut Microbes. 2025 Dec;17(1):2446374. doi: 10.1080/19490976.2024.2446374. Epub 2024 Dec 26. PMID: 39722590.